Medical Disclaimer
This article, including information addressing Is Carisoprodol still prescribed?, is intended for educational purposes only and does not constitute medical advice. Carisoprodol carries documented risks such as sedation, dependence, and impaired alertness, particularly when combined with alcohol, benzodiazepines, or opioids. It is metabolized into meprobamate, which may contribute to prolonged effects in some individuals. Use should always follow the guidance of a licensed healthcare professional and is generally limited to short-term treatment as determined by a physician.
Patients exploring pain-management options frequently encounter conflicting information about older muscle relaxants—prompting a common and important question: Is Carisoprodol still prescribed? Some sources describe it as effective for short-term muscle discomfort, while others emphasize safety risks, tighter regulations, or reduced availability. This mixed messaging can make it challenging for patients and caregivers to understand Carisoprodol’s role in modern medicine and whether safer alternatives are now preferred.
This educational guide explains current prescribing practices, regulatory status, safety concerns, and modern alternatives, helping readers understand how Carisoprodol fits into today’s pain-management landscape.
What Is Carisoprodol and Why Was It Prescribed?
Carisoprodol is a centrally acting skeletal muscle relaxant historically prescribed for short-term relief of discomfort associated with acute musculoskeletal conditions, such as back pain, neck strain, or muscle spasms. Unlike medications that act directly on muscle tissue, Carisoprodol works by influencing nerve communication in the brain and spinal cord, producing generalized muscle relaxation and sedation.
When introduced in the late 1950s, Carisoprodol became widely used because it appeared to reduce muscle tension and allow patients to rest during injury recovery. For decades, it was commonly prescribed alongside rest, limited activity, and physical therapy.
However, as prescribing increased, clinicians observed effects beyond muscle relaxation. Sedation, dizziness, slowed reaction time, and impaired coordination were increasingly reported—raising concerns about safety, particularly with prolonged or unsupervised use.
Key Takeaways
- Carisoprodol was developed for short-term treatment of acute muscle pain
- Its effects occur via the central nervous system
- Longstanding use prompted closer safety evaluation
Is Carisoprodol Still Prescribed Today?
Is Carisoprodol still prescribed? Yes—but far less commonly than in the past. In the United States, prescribing has declined sharply due to evolving safety data, regulatory changes, and the availability of muscle relaxants with more predictable risk profiles.
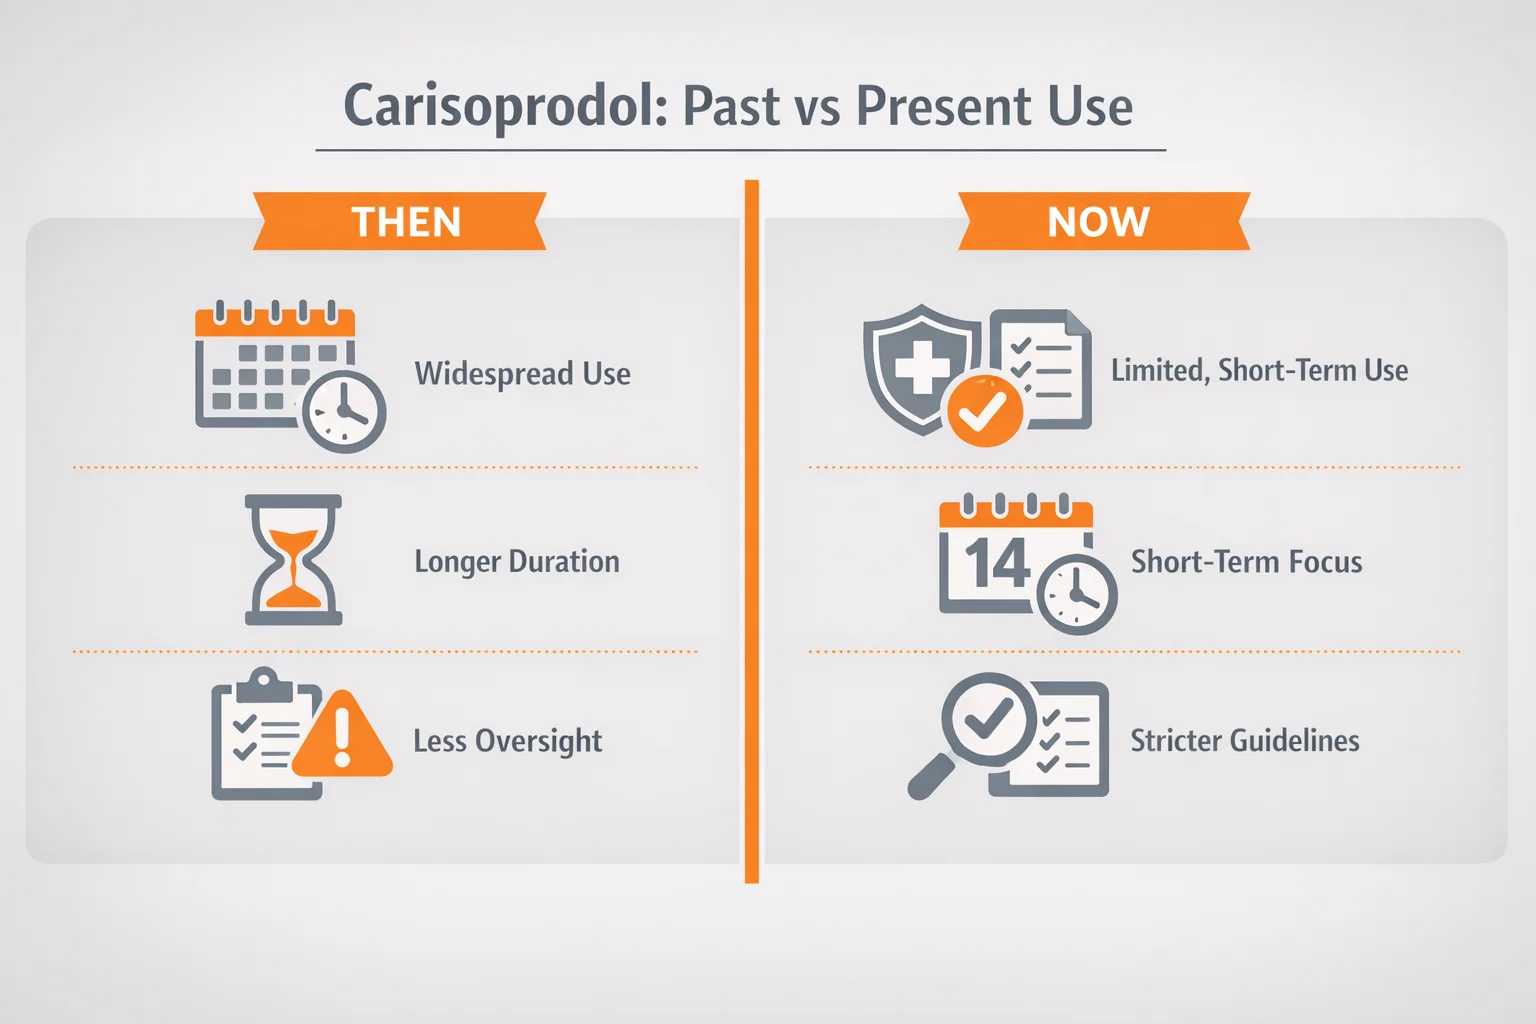
Some healthcare providers may still prescribe Carisoprodol in limited, short-term situations, particularly when other therapies are ineffective or unsuitable. However, most modern guidelines recommend trying alternatives first.
Internationally, prescribing practices vary. In several countries, Carisoprodol has been restricted or removed from routine use altogether, reflecting a global shift toward safer pain-management strategies.
Patients researching availability often encounter resources such as Carisoprodol (Soma) availability today, which highlight that access exists but within a more regulated framework.
Key Takeaways
- Carisoprodol use has declined significantly
- Current prescribing is selective and short-term
- Global trends favor safer alternatives
FDA Schedule IV Classification and Regulatory Oversight
A major turning point in Carisoprodol’s clinical use occurred when it was classified as a Schedule IV controlled substance by the Food and Drug Administration. This classification recognizes legitimate medical use while acknowledging potential risks related to misuse or dependence.

Oversight is coordinated with the Drug Enforcement Administration, which categorizes Schedule IV medications as having lower abuse potential than Schedule II or III drugs, but still requiring regulation.
Authoritative references such as Schedule IV controlled substance classification explain why medications in this category are monitored more closely.
Why Was This Classification Necessary?
One key reason is that Carisoprodol is metabolized into meprobamate, a compound associated with sedative effects and dependence risk. Detailed pharmacological discussions, including Metabolism into meprobamate and dependence risk, outline why this conversion raised concerns.
Additionally, safety reviews documented adverse effects such as excessive sedation, impaired driving ability, and withdrawal symptoms when the medication was stopped abruptly.
Patients seeking neutral drug education can consult Carisoprodol safety and side-effect information for balanced, evidence-based guidance.
Key Takeaways
- Carisoprodol is a Schedule IV medication
- Meprobamate metabolism contributes to risk concerns
- Regulation reflects risk management, not routine use
How Does Carisoprodol Compare to Safer Modern Alternatives?
Modern pain-management guidelines emphasize medications with lower misuse potential and clearer safety profiles. While no muscle relaxant is entirely risk-free, clinicians today often consider other options before Carisoprodol.
Institutions such as the Mayo Clinic emphasize Short-term use recommendations for muscle relaxants and careful patient selection.
Educational content on GlobalPharmacare’s pain-management blog reflects these modern standards, focusing on safety, tolerance, and individualized care rather than routine prescribing.
Patients frequently research dosage-related topics online, encountering discussions such as 350 mg Soma dosage and safety considerations. These resources reinforce why medical supervision is essential and why Carisoprodol is typically not a first-line option.
Key Takeaways
- Newer muscle relaxants are generally preferred
- Safety and tolerability guide prescribing decisions
- Treatment selection is individualized
Non-Opioid and Non-Drug Pain-Management Approaches
Medication is only one component of effective pain management. Many contemporary guidelines emphasize non-pharmacological strategies, either alone or alongside medication, particularly for musculoskeletal pain.
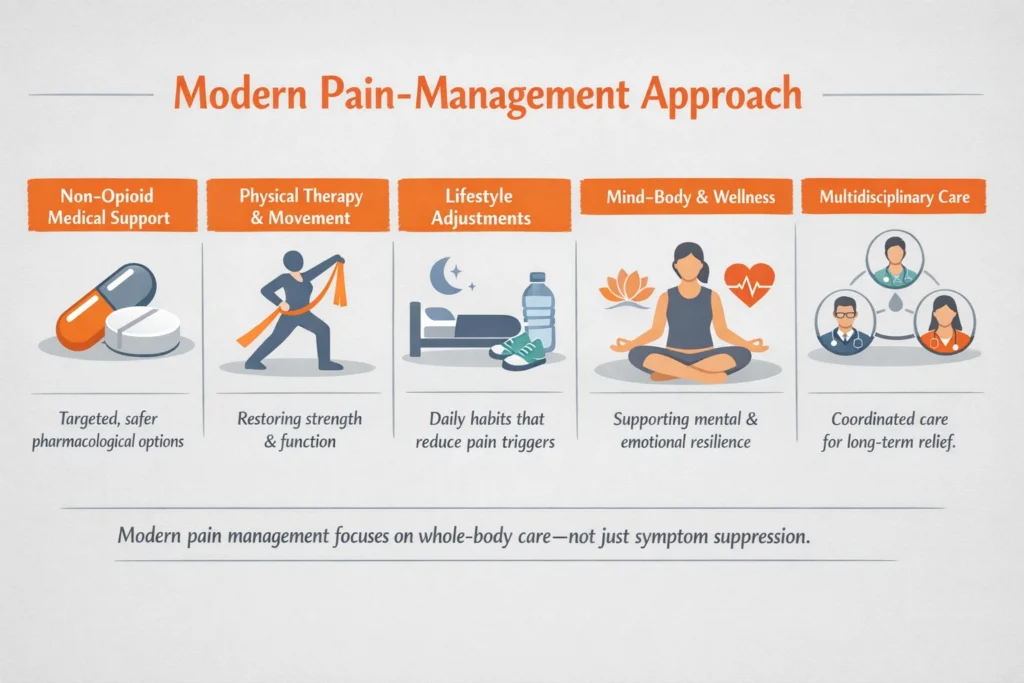
Common approaches include:
- Physical therapy and guided exercise
- Ergonomic adjustments at work or home
- Heat, cold, or manual therapy
- Mind-body techniques such as relaxation training
Authoritative guidance such as Non-drug approaches to managing musculoskeletal pain highlights how these strategies address movement patterns and functional limitations rather than simply masking symptoms.
Educational overviews on GlobalPharmacare’s pain-management pages also stress the importance of comprehensive, individualized plans.
Key Takeaways
- Non-drug approaches are central to modern pain care
- Combining strategies may support better long-term outcomes
- Education and professional guidance are essential
Frequently Asked Questions About Carisoprodol
Yes. Is Carisoprodol still prescribed? It remains legal but is tightly regulated and used far less often than in previous decades.
Concerns include sedation, dependence risk, and the availability of alternatives with more favorable safety profiles.
It is generally not recommended for long-term or chronic pain, as guidelines emphasize safer, sustainable approaches.
No. Physical therapy, lifestyle modifications, and other non-drug strategies are often recommended as first-line options.
Pharmacy-backed and educational platforms, such as GlobalPharmacare, provide neutral, up-to-date resources.
Conclusion
Carisoprodol once played a meaningful role in the management of acute musculoskeletal pain, particularly at a time when fewer treatment options were available. However, as clinical understanding has evolved, modern medicine has increasingly shifted toward safer, more predictable, and better-studied approaches to pain management. While the answer to “Is Carisoprodol still prescribed?” is technically yes, its use today is far more limited than in previous decades.
Regulatory classification, documented safety concerns, and updated clinical guidelines have all contributed to a significant reduction in routine prescribing. Healthcare providers now carefully weigh potential risks against potential benefits and typically consider Carisoprodol only in select, short-term situations when other options are not appropriate.
Today’s pain-management strategies emphasize individualized treatment plans, prioritizing non-opioid medications, non-drug therapies, and patient education. This approach reflects a broader focus on long-term safety, functional improvement, and informed decision-making—guided by licensed healthcare professionals rather than one-size-fits-all solutions.
Actionable Steps
- Discuss all pain-management options with a qualified professional
- Ask about both medication and non-drug approaches
- Use reputable educational platforms such as GlobalPharmacare
- Avoid making medication decisions without medical guidance
Author Note
Paul Harris is a clinical consultant with over 15 years of experience in musculoskeletal pharmacology and controlled substance regulation. His work emphasizes patient safety, evidence-based analysis of CNS depressants, and the transition from legacy medications to modern, lower-risk pain-management strategies. Paul advocates for multidisciplinary pain care, combining pharmaceutical insight with physical and psychological wellness approaches to support informed, responsible decision-making.